


Menopausal skin changes: what happens and what can help
Doctor-led assessment in Hale, Cheshire
Menopausal skin changes · Hale, Cheshire

Menopausal skin does not change in one predictable way. During perimenopause, skin can become dry and reactive while also developing spots, flushing or uneven pigment. Later, it may feel thinner, recover more slowly and show lines or laxity that seem to have arrived quite quickly. Falling and fluctuating oestrogen can contribute, but sun exposure, genetics, skincare, medication and general health still matter.
At our Hale clinic, we do not start by deciding which laser you need. We work out which part of the picture is most important: an unsettled skin barrier, redness, acne, pigmentation, rough texture, collagen change, volume loss or a mixture. Sometimes the best first step is a simpler skincare routine. Sometimes a device or injectable treatment is sensible. And sometimes a new symptom belongs with your GP or dermatologist rather than an aesthetic treatment.
Hale clinic · Consultation first
You do not need to choose a treatment before contacting us. We start by understanding the cause, then explain whether a clinic pathway, observation or a referral is the more sensible next step.
At a glance
How we think about menopausal skin changes
 Assessment focus
Dryness, itching, sensitivity, flushing, breakouts, pigmentation, texture, lines, laxity and hair change; when each began; perimenopause or menopause symptoms; HRT and other medicines; skincare, sun history and previous treatment.
 Possible pathways
Barrier repair and personalised skincare; medical acne or dermatology care; BBL® HEROic™, MOXI®, BBL HEROic and MOXI, ClearSilk®, ClearV®, SkinPen®, HALO® TRIBRID™ or Erbium resurfacing for suitable concerns; carefully chosen injectable or tightening treatment; or observation and home care.
 Our approach
Treat the component that is actually present. Stabilise inflamed or over-treated skin before adding energy, and match treatment depth to the concern and the recovery you can accommodate.
 Medical care first
A new or changing pigmented lesion, a sore that bleeds or does not heal, widespread unexplained itch, a severe rash, sudden hair loss or another rapid unexplained change needs GP or dermatology assessment. We do not provide mole checks.
What this concern can involve
Oestrogen has a role in the skin’s hydration, barrier function, collagen, elasticity, blood vessels and healing response. As levels fluctuate in perimenopause and fall after menopause, skin may hold less water and feel drier. Collagen support and elasticity can reduce, while years of accumulated sun exposure become more visible. This is one reason changes can feel sudden even though ageing and photodamage have been developing for much longer.
Menopausal skin changes can include:
Dryness, tightness and itching
Skin may produce less oil, lose water more readily and become less tolerant of products that previously caused no problem.
Sensitivity and a disrupted barrier
Stinging, burning or flaking is often made worse by adding more acids, scrubs or high-strength retinoids to an already unsettled routine.

Flushing, redness and rosacea
Heat, hot flushes and vascular reactivity can make redness more noticeable. Not every flush is rosacea, and not every red face needs a laser.
Adult acne
Hormonal fluctuation can contribute to jawline spots or a return of breakouts, sometimes at the same time as the skin becomes drier. Treating it like oily teenage skin can be too harsh.
Pigmentation and uneven tone
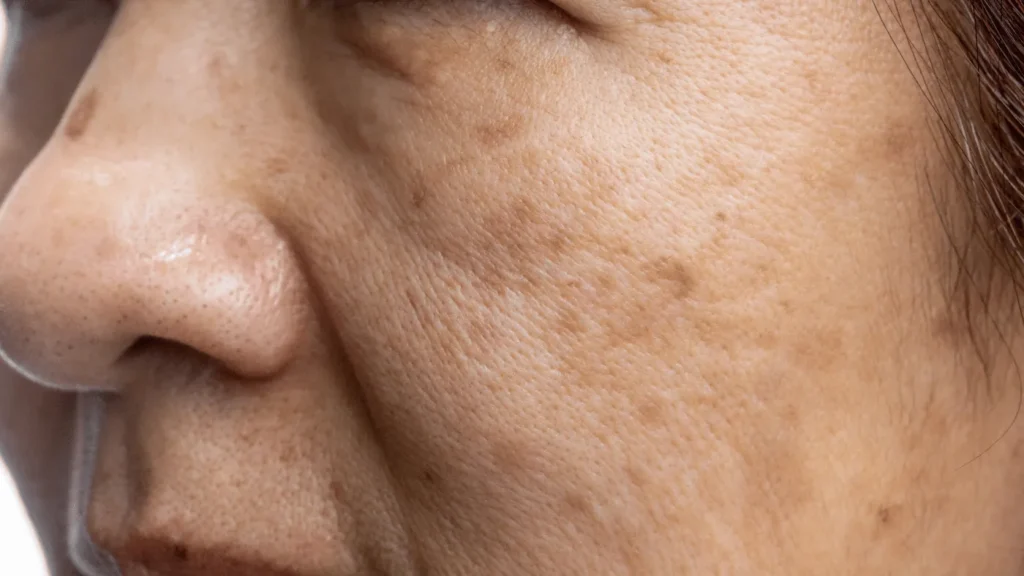
Sun spots, mottled pigmentation and redness can become more visible as skin changes. Melasma and post-inflammatory pigment need a more cautious plan than an isolated sun spot.

Fine lines, roughness and visible pores
Reduced hydration can exaggerate fine lines; collagen change and photodamage contribute to more established texture.
Laxity, crepiness and volume change
The skin, fat compartments, ligaments and bone all change with age. A surface treatment cannot replace support that has changed more deeply.
Easier bruising or slower recovery
Skin may become more fragile, but unexplained bruising or poor healing should not automatically be blamed on menopause.

More facial hair and less scalp density
These changes can occur together as hormone balance shifts. They have separate assessment and treatment pathways.
Not every change that happens in your forties or fifties is caused by menopause. Eczema, rosacea, acne, thyroid disease, iron deficiency, medication, weight change, smoking, stress and cumulative UV exposure may overlap. A useful assessment holds those possibilities in mind rather than using “hormones” as a catch-all explanation.
How we assess it
We ask what changed first, how quickly it changed and which symptom is genuinely affecting you. Tell us whether you are in perimenopause, have reached menopause or are unsure; you do not need a hormone test simply to describe your skin. We review HRT, contraception, other medicines and supplements, but we do not advise you to start or stop HRT for cosmetic reasons.
We look at the skin in good light and assess barrier condition, inflammation, vascular redness, pigment pattern, texture, scarring, lines and laxity. Skin analysis can provide useful images and a baseline, but it does not diagnose every rash or replace medical examination. We also ask about sun exposure, smoking, previous procedures, cold sores, pigment reactions and the amount of recovery you can realistically accommodate.
The assessment should lead to priorities. If your skin is burning and peeling from an overloaded routine, another active product or laser is unlikely to be the best first move. If the barrier is stable but colour and texture have changed at different depths, a combination plan may make sense. If a lesion is new, changing or suspicious, diagnosis comes before cosmetic treatment.

Assessment pathway
A useful consultation for menopausal skin changes follows a clear sequence rather than jumping to a product.
History
What changed first, how quickly, and which symptom matters most to you.
Examination
Barrier, redness, pigment, texture, lines and laxity, assessed in good light.
Priorities
Which component to treat first, and whether anything needs medical review.
Plan
Skincare, a device or injectable treatment, a staged plan, observation or referral.
Your consultation
You do not need to choose a treatment before contacting us. Tell us what you have noticed, when it changed, what you have already tried and what a worthwhile result would look like to you. We consider your health, medication, previous procedures, skin characteristics and practical tolerance for recovery.
A useful consultation may lead to treatment, a staged plan, a period of observation or a referral. We would rather explain that an option is unlikely to help than place you into a course simply because the treatment is available.

Options we may discuss
Menopausal skin changes have more than one cause, so there is no single fix. The right option depends on what we find at consultation.





What treatment may realistically achieve
A good plan can improve a defined concern: calmer redness, clearer pigment, smoother texture, fewer breakouts, better hydration or softer lines. It cannot return skin to a pre-menopausal state, stop chronological ageing or prevent future sun damage. Skin quality is a collection of features, so one treatment rarely changes every feature to the same degree.
Results also have different time courses. Hydration may improve relatively quickly when an irritating routine is corrected. Pigment and vascular change may need a course and careful maintenance. Collagen remodelling develops over weeks to months. More intensive resurfacing may create a more noticeable change but brings more recovery and does not remove every line or scar.
Maintenance is part of skin care, not evidence that the first treatment failed. Daily sunscreen, a tolerable routine, management of an underlying skin condition and periodic review often matter more than repeating a procedure by habit. We agree how progress will be photographed and when it is reasonable to judge the result.
Related concerns we may also discuss
Menopausal skin changes often sit alongside other related findings. These related concerns help frame the wider assessment.






Comfort, safety and clinical judgement
Comfort planning depends on the treatment. It may include cooling, topical anaesthetic, local anaesthetic, pacing or a nerve block for some procedures. We explain the expected sensation and visible recovery in advance. Anaesthesia can improve comfort; it does not remove the possibility of burns, pigment change, infection, scarring, bruising or another procedure-specific complication.
Menopausal skin is not automatically too fragile for treatment, but dryness, inflammation, medication, recent tanning, cold-sore history, pigment tendency and healing history can change the plan. Safety begins with a stable diagnosis, suitable selection and sensible timing. Device choice, wavelength, energy, treatment depth, eye protection, sterile technique and aftercare are matched to the individual.
If your skin is already inflamed or over-treated, postponing a procedure can be the safest recommendation. We would rather settle the barrier and treat from a stronger starting point than create a longer recovery for the sake of keeping an appointment date.
Nerve blocks and comfort
Laser, light and microneedling treatments can be uncomfortable. Topical anaesthetic, cooling and a paced approach are discussed beforehand, and a nerve block may be offered for some treatments where clinically appropriate.
Ultrasound as a clinical tool
For some injectable treatments, ultrasound can help answer an anatomical question or guide aspects of treatment. It supports clinical judgement; it does not remove the risks of treatment, and it is not relevant to every menopause-related skin concern.
Medical thinking
Why choose Dr Ed Robinson Clinics
Our approach is medical, conservative and consultation-led. We have several devices and treatment types available, which means the consultation is not built around forcing one machine to address every menopause-related change. We can separate colour from texture, surface dryness from structural change and a cosmetic concern from a symptom that needs wider healthcare.
Cause before product
We separate colour from texture, surface dryness from structural change and a cosmetic concern from a symptom that needs wider healthcare.
Comfort planned with judgement
Comfort planning may include topical or local anaesthetic, cooling, paced treatment or a nerve block where clinically appropriate.
Honest next steps
A useful consultation may lead to treatment, observation or a referral. We would rather explain when an option is unlikely to help.
CQC Good · Hale registered service
The registered Hale service is rated Good overall and Outstanding in leadership by the CQC. That rating relates to the registered service at Hale; it should not be read as separate CQC approval of every cosmetic procedure.
Read the CQC report for the registered Hale service · Meet Dr Ed
What you can do at home
Start with the routine you can tolerate consistently:
Sleep, smoking, alcohol, nutrition and sun exposure influence skin and general health, but no supplement can be guaranteed to replace lost collagen or correct a hormonal skin change. Tell us about supplements before treatment, particularly if they affect bleeding or interact with medication.
When to seek medical advice
A new or changing pigmented lesion, a sore that repeatedly bleeds, a crusted area that does not heal or a rapidly growing lump needs medical assessment before any cosmetic treatment. We do not provide mole-checking services. Please contact your GP or an appropriate dermatology service.
Persistent widespread itch, a severe or spreading rash, blistering, fever, unexplained bruising, marked swelling or skin pain also needs medical review. Sudden scalp hair loss, rapid facial hair growth or a major change in acne alongside other hormonal symptoms should not simply be attributed to menopause.
Vulval burning, soreness, bleeding, a new lesion or urinary symptoms belong with your GP, sexual-health or menopause service. They should not be diagnosed from a facial-skin consultation or treated with a cosmetic product without assessment.
Related videos, articles and results
Further reading and clinic media that can help you understand menopausal skin changes in context.



Frequently asked questions
What happens to your skin during perimenopause and menopause?
Fluctuating and falling oestrogen can affect hydration, oil production, barrier function, collagen, elasticity, blood vessels and healing. You may notice dryness, itching, sensitivity, flushing, acne, uneven pigment, lines or laxity. Genetics, sun exposure, medication and skin conditions still contribute, so the pattern is individual rather than inevitable.
When do menopausal skin changes start?
They can begin during perimenopause, before periods stop completely. Some changes fluctuate with other symptoms; others become more noticeable after menopause. There is no single age or sequence, and a new symptom should not be dismissed purely because it began in midlife.
Why is my skin suddenly so dry and itchy?
Skin can hold less water and produce less oil around menopause, which weakens the barrier and makes previous products feel irritating. Hot showers, fragranced cleansers, over-exfoliation and dry environments can add to the problem. Widespread or persistent itch can also have other causes, especially when there is no obvious rash, and should be discussed with your GP.
Can menopause cause acne?
Yes. Hormonal fluctuation can contribute to adult acne, often around the lower face and jaw, even while the rest of the skin feels dry. A barrier-friendly routine and appropriate medical treatment are usually more useful than aggressive scrubbing. Deep, painful or scarring acne deserves assessment.
Can menopause make rosacea or flushing worse?
Hot flushes and vascular reactivity can make facial warmth and redness more noticeable, and established rosacea may feel less predictable. Not every flush is rosacea. We assess background redness, visible vessels, spots, sensitivity and triggers before deciding whether skincare, medical care, ClearSilk, BBL HEROic or ClearV is the most relevant route.
Does menopause cause pigmentation?
Hormonal change can influence pigment, but much of the visible brown change in midlife reflects cumulative UV exposure. Melasma, sun spots and pigment left by inflammation behave differently. A diagnosis matters because an overly aggressive light or laser treatment can worsen some pigment patterns.
Does collagen decrease during menopause?
Yes. Oestrogen decline is associated with reduced collagen production, skin thickness and elasticity, although the amount and visible effect vary. Sun exposure and smoking also accelerate collagen breakdown. Skincare and procedures may improve aspects of texture or firmness, but they cannot restore every structural change or stop ageing.
Why do I have more facial hair but thinner scalp hair?
The change in hormone balance around menopause can make some facial follicles more active while scalp follicles become finer. These are not treated in the same way. Read our guides to unwanted facial hair and hair loss, and seek medical advice if either change is sudden or marked.
What is the best skincare routine for menopausal skin?
There is no universal menopause range. A useful core is a gentle cleanser, a moisturiser suited to your barrier and daily broad-spectrum sunscreen. Antioxidants, retinoids, pigment treatments or acne products can be added according to the concern and tolerance. A shorter routine used consistently is usually better than a complicated one that keeps the skin inflamed.
Can I use retinol or tretinoin during menopause?
Many patients can, but drier or more reactive skin may need a lower strength, slower introduction or a different formulation. Tretinoin is a prescription medicine and should be used with appropriate advice. Stop and seek guidance if you develop persistent burning, swelling, cracking or dermatitis rather than trying to “push through” it.
Will collagen supplements fix menopausal skin?
Some studies report modest benefits from particular hydrolysed collagen products, but products and evidence vary, and no supplement can be guaranteed to rebuild facial structure or replace oestrogen. Supplements should not take the place of sunscreen, a tolerable routine, adequate nutrition or medical assessment. Tell your clinician what you take before a procedure.
Does HRT improve skin and collagen?
HRT may affect hydration, collagen and skin thickness in some patients, but it is prescribed for menopause symptoms and health considerations, not as a cosmetic anti-ageing treatment. The decision depends on your symptoms, age, medical history and individual risks. Discuss it with your GP or menopause clinician rather than starting HRT for appearance alone.
Can I have laser treatment while taking HRT?
HRT itself is not an automatic reason to avoid every laser or light treatment. We still need to know the preparation, other medication, pigment history, skin condition, recent tanning and the exact device proposed. A consultation and patch testing are used where appropriate; do not stop prescribed HRT simply to have a cosmetic procedure.
Which treatment is best for menopausal skin?
There is no single best treatment because “menopausal skin” can mean dryness, redness, acne, pigment, texture, laxity or volume change. Skincare may be the correct first step for barrier symptoms; BBL HEROic may suit colour, MOXI early texture, ClearSilk diffuse redness, HALO or Erbium more established resurfacing, and an injectable or tightening treatment a deeper structural concern. The assessment decides the route.
What is the difference between BBL HEROic, MOXI and HALO for menopausal skin?
BBL HEROic is primarily colour-focused and may address some pigment or redness. MOXI is a gentler fractional laser for early texture and tone. HALO TRIBRID can combine superficial and deeper resurfacing for more established texture, lines, pores, pigmentation or some scarring, with more recovery. They are not simply weak, medium and strong versions of the same treatment.
Can menopausal skin treatments be used on the neck, chest and hands?
Often, yes, but the skin thickness, sun exposure and healing pattern differ by area. BBL HEROic, MOXI, HALO, Erbium, injectables or tightening treatments may be considered for some concerns on the neck, décolletage or hands. Settings and recovery should not simply be copied from the face.
How long do results last?
It depends on what is treated. A corrected barrier needs ongoing care. Pigment and redness can recur with sun exposure, hormones and vascular triggers. Collagen remodelling develops over months, while ageing continues. We explain the likely course, maintenance and home routine for the specific treatment rather than giving one lifespan for “menopausal skin results”.
Can treatments restore the skin I had before menopause?
No treatment can return skin to an earlier age or prevent future change. The sensible aim is improvement in the feature that matters to you while preserving expression and keeping recovery proportionate. Clearer tone, smoother texture, better hydration or softer lines can be worthwhile without pretending the biology has been reversed.
When should a menopausal skin change be checked by a doctor?
Seek medical assessment for a new or changing pigmented lesion, a bleeding or non-healing sore, severe or widespread itch, a persistent rash, unexplained bruising, sudden hair loss or rapid facial-hair growth. We do not provide mole checks; suspected or changing lesions should go to your GP or an appropriate dermatology service.